
Repolarization & channelopathies
Brugada pattern, type 1
An inherited sodium-channel disorder that shows as coved ST elevation in V1–V2. The heart is structurally normal but prone to ventricular fibrillation.
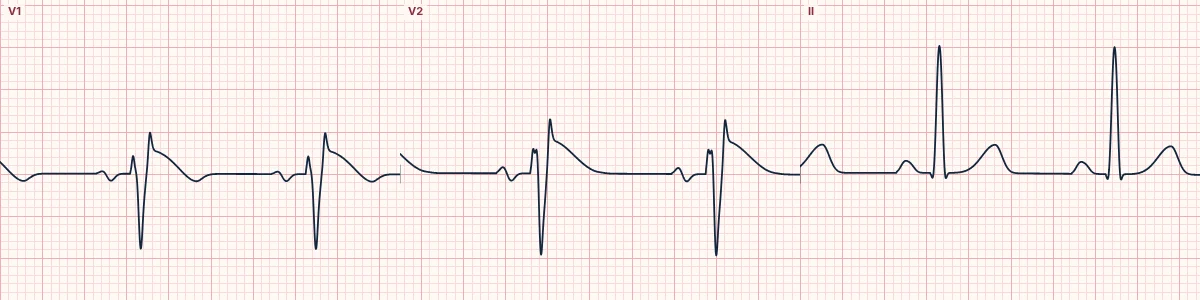
What the heart is doing
Reduced sodium current leaves outward currents unopposed in the right ventricular outflow tract's outer layer. The resulting voltage gradient across the wall raises the ST segment in V1–V2.
Why it looks this way
This is the Brugada type 1 pattern because V1–V2 show coved ST elevation of at least 2 mm descending into an inverted T wave.
Why it matters
With syncope, nocturnal gasping, family sudden death or documented arrhythmia it is Brugada syndrome, with a risk of sudden death. Treat fever, avoid provoking drugs and refer urgently.
What to look for
- In V1–V2, the ST rises high at the J point and descends in a convex curve to a negative T wave.
- Check I and V6: without a wide terminal S wave, this is not a true RBBB.
- Moving V1–V2 up one or two rib spaces can unmask the pattern.
Frequently asked questions
What are the ECG criteria for brugada pattern, type 1?
V1–V2: coved ST elevation ≥ 2 mm, sloping down into an inverted T wave. Leads: at least one of V1 or V2. QRS: pseudo-RBBB shape without a wide S wave in I or V6. Other leads: normal.
How is brugada pattern, type 1 identified on an ECG?
This is the Brugada type 1 pattern because V1–V2 show coved ST elevation of at least 2 mm descending into an inverted T wave.
What can brugada pattern, type 1 be mistaken for?
RBBB: rsR′ in V1 with a wide S in I and V6 and no coved elevation. Anteroseptal STEMI: chest pain, elevation extending to V3–V4, reciprocal changes. Early repolarization: concave ST elevation with an upright T wave.
What causes brugada pattern, type 1?
Common causes: inherited sodium-channel variants; unmasked by fever; unmasked by sodium-channel blocking drugs; unmasked by alcohol or cocaine; and more common in men and in Southeast Asian populations.