
Electrolytes
Hyperkalemia, mild (peaked T waves)
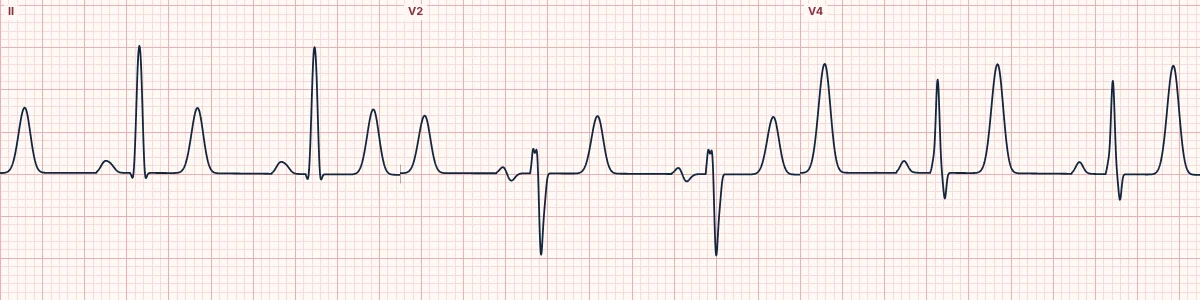
The earliest ECG sign of a raised blood potassium: tall, narrow, pointed T waves, while the P wave and QRS still look normal.
What the heart is doing
Extra potassium outside the cells speeds up repolarization. The T wave, which records repolarization, becomes taller, narrower and more symmetric before conduction itself is affected.
Why it looks this way
This is mild hyperkalemia because the T waves are tall, narrow and symmetric across many leads while the P waves and QRS remain normal.
Why it matters
The ECG tracks the potassium level poorly and can deteriorate quickly. Any change in an at-risk patient calls for urgent confirmation, continuous monitoring and treatment to protect the heart and lower potassium.
What to look for
- T waves with a narrow base and a sharp peak, as if pinched upward.
- The change is widespread, not confined to one coronary territory.
- Compare with an old ECG; a T taller than the R wave in several leads is suspicious.
Frequently asked questions
What are the ECG criteria for hyperkalemia, mild (peaked T waves)?
T waves: tall, narrow, symmetric ('tented'), best in V2–V4. QT: normal or short. P waves: normal. QRS: normal width.
How is hyperkalemia, mild (peaked T waves) identified on an ECG?
This is mild hyperkalemia because the T waves are tall, narrow and symmetric across many leads while the P waves and QRS remain normal.
What can hyperkalemia, mild (peaked T waves) be mistaken for?
Hyperacute T waves of early STEMI: broad-based and limited to one territory. Early repolarization: tall T waves with J-point elevation. de Winter pattern: tall T waves that begin from a depressed J point.
What causes hyperkalemia, mild (peaked T waves)?
Common causes: kidney failure or missed dialysis; ACE inhibitors, potassium-sparing diuretics; acidosis, including diabetic ketoacidosis; tissue breakdown (crush injury, rhabdomyolysis, burns); and adrenal insufficiency.