
Coronary occlusion (STEMI)
Left main coronary insufficiency
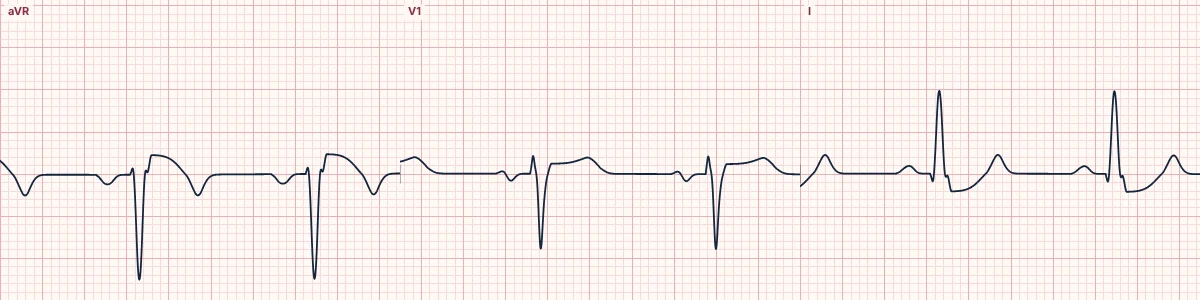
aVR elevation with diffuse ST depression
Critically reduced flow in the left main coronary artery (LMCA), which feeds most of the left ventricle. It causes widespread inner-wall ischemia and not a localized transmural infarct.
What the heart is doing
The inner layer of the whole left ventricle is ischemic. Its ST vector points from the muscle toward the cavity, up and to the right, so aVR records elevation and most other leads depression.
Why it looks this way
This is left main insufficiency because ST elevation in aVR (greater than V1) accompanies ST depression in six or more other leads.
Why it matters
In a patient with ischemic symptoms this marks a very high-risk coronary lesion needing urgent angiography. The same pattern can come from severe demand ischemia, so correct hypoxia, anemia and tachycardia too.
What to look for
- Widespread horizontal or downsloping ST depression with the ST raised in aVR.
- Count the leads with depression; six or more with aVR elevation is the pattern.
- Do not ignore aVR; it is the only lead facing the cavity of the heart.
Frequently asked questions
What are the ECG criteria for left main coronary insufficiency?
Artery: left main (or equivalent multivessel disease). ST elevation: aVR, V1. ST depression: I, II, aVL, aVF, V3, V4, V5, V6. Pattern: elevation in aVR ≥ 1 mm and greater than in V1. Extent: ST depression in 6 or more leads.
How is left main coronary insufficiency identified on an ECG?
This is left main insufficiency because ST elevation in aVR (greater than V1) accompanies ST depression in six or more other leads.
What can left main coronary insufficiency be mistaken for?
Demand ischemia from rapid SVT, sepsis or anemia: resolves when the trigger is treated. Left ventricular hypertrophy with strain: depression confined to lateral leads. Digoxin effect or hypokalemia: scooped ST or U waves without symptoms.
What causes left main coronary insufficiency?
Common causes: left main coronary stenosis; proximal LAD stenosis; severe three-vessel coronary disease; global demand ischemia (tachyarrhythmia, anemia, hypoxia, shock); and aortic dissection involving the left main.